
Hemophilia overview
 Fact-checked by
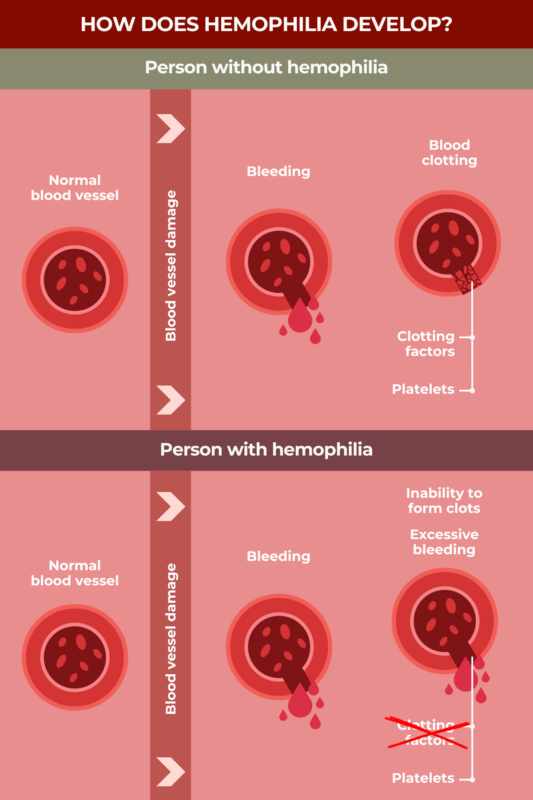
Hemophilia is a rare disorder in which a person’s blood is not able to clot properly, resulting in prolonged bleeding after injuries or bleeding without an obvious cause.
Normally, proteins called clotting factors help form clots to prevent excessive bleeding after an injury. In people with hemophilia, one of these proteins either does not work properly or not enough of it is made, leaving individuals prone to abnormal bleeding. The most common forms of the disease are caused by genetic mutations and primarily affect boys and men.
There is no cure for hemophilia, but there are several available therapies to help prevent and control bleeding episodes. With these modern treatments, many people with hemophilia can have a normal or near-normal life expectancy.
Scroll horizontally to view all columns -->
| Question | Short answer |
|---|---|
| What causes hemophilia? | Usually, an inherited genetic mutation |
| What are the main types? | Hemophilia A, B, and C |
| What is the main symptom? | Prolonged bleeding after injury or spontaneous bleeding |
| How is it diagnosed? | Blood-clotting tests |
| Is it treatable? | Yes — preventive and on-demand therapies can reduce and control bleeding |
| Is it curable? | No — most treatments manage the disease, but do not eliminate it permanently |
Causes
In most cases, hemophilia is caused by mutations in genes that produce certain clotting factors. These genetic changes mean that not enough of the clotting factor is made, or the version produced does not work properly. The specific gene that is mutated determines the type of hemophilia a person has:
- Hemophilia A: F8 gene, which encodes clotting factor VIII (FVIII)
- Hemophilia B: F9 gene, which encodes clotting factor IX (FIX)
- Hemophilia C: F11 gene, which encodes factor XI (FXI)
Babies are born with these mutations, which are inherited from a person’s biological parents in about two-thirds of cases. In the remaining cases, there may be no family history of the disease. This can be due to spontaneous mutations that occur during the early development of an individual sperm or egg cell involved in conceiving the child.
The F8 and F9 genes are both located on the sex-determining X chromosome and are thus inherited differently in males and females. Hemophilia A and B predominantly affect boys and men. F11 is not on a sex-determining chromosome, and hemophilia C affects the sexes equally.
People who carry one copy of a gene with a hemophilia-causing mutation and a second healthy copy of the gene usually won’t develop severe overt symptoms of the disease, but can pass the mutation on to their children.
There are other uncommon hemophilia causes. Rarely, a person can develop hemophilia later in life. This is not caused by genetic mutations, but arises when the immune system malfunctions and mistakenly attacks a clotting factor.
Types
There are three main types of hemophilia:
- hemophilia A: the most common type caused by an FVIII deficiency
- hemophilia B: the second-most common type caused by an FIX deficiency
- hemophilia C: a rare type caused by an FXI deficiency
While these disease types differ in the affected clotting factor and inheritance pattern, they can generally cause the same bleeding symptoms. All three may be classified as mild, moderate, or severe based on the extent of the clotting factor deficiency and the risk of serious or spontaneous bleeds. Hemophilia A and B are more likely to be severe than hemophilia C, and are thus also more likely to require regular treatment.
The very rare cases in which hemophilia arises from an immune system malfunction rather than a genetic mutation are known as acquired hemophilia. In most cases, FVIII is the target of these immune attacks. Disease severity can vary widely.
Symptoms
The main symptom of hemophilia is abnormal bleeding. This can include bleeding that lasts longer than usual after an injury or medical procedure, or spontaneous bleeding without an obvious cause. Bleeding can occur externally or internally. Possible forms of external bleeding include:
- prolonged bleeding after even minor injuries, like cuts and scrapes, or bleeding that restarts after it has been controlled
- unusual bleeding after medical procedures that puncture the skin, such as vaccination, circumcision, or dental procedures
- frequent or difficult-to-control nosebleeds
- heavy or prolonged menstrual bleeding
Internal bleeding in hemophilia most often includes:
- excessive bruising from bleeding under the skin
- hematomas, or bleeding in the deeper layers under the skin, which can cause lumps
- bleeding into the joints or muscles, which can cause pain and mobility issues
Recurrent bleeding into the joints can cause hemophilic arthropathy, characterized by permanent, irreversible joint damage. Bleeds in certain muscles can also lead to complications, including serious blood loss and nerve compression.
Bleeding within internal organs can lead to a wide range of other symptoms. These include:
- blood in the urine or stool
- vomiting or coughing up blood
- abdominal pain
- urinary changes
- neurological changes, including vision issues, headaches, confusion, weakness, and seizures
The exact hemophilia symptoms depend on a person’s hemophilia severity, which is determined by how significantly clotting factor activity is diminished. While people with milder forms of hemophilia may bleed longer than usual after an injury or medical procedure, people with severe hemophilia may be more prone to spontaneous bleeding or more serious types of internal bleeds.
Diagnosis
Hemophilia is diagnosed mainly through clotting factor tests, also called factor assays. These blood tests measure the activity of individual clotting proteins to identify which one is deficient, and to what degree, which informs the hemophilia type and severity.
Other screening tests can help establish a hemophilia diagnosis and rule out other bleeding disorders. These include:
- a complete blood count, to assess the numbers and health of blood cells
- blood-clotting tests, to look at how well and how quickly the blood clots
- a Bethesda assay, to identify neutralizing antibodies against clotting factors that are present in acquired hemophilia
Because hemophilia is inherited in most cases, determining whether an individual has a family history of the disease can also help establish the diagnosis. For expectant parents at risk of having a child with hemophilia, genetic testing can be performed during pregnancy to determine whether the baby has a disease-causing mutation.
Treatment
There are several treatments available to help prevent and control bleeding in hemophilia A and B. Depending on a person’s hemophilia type, severity, and their risk of serious bleeding, hemophilia treatment may be given in two ways:
- on-demand: as needed to control active bleeds
- prophylaxis: on a regular basis to prevent bleeds
In general, routine prophylaxis is recommended for people with severe hemophilia and may also be considered for some people with mild or moderate hemophilia. Major classes of hemophilia therapies include:
Scroll horizontally to view all columns -->
| Treatment approach | What it does |
|---|---|
| Factor replacement therapy | Replaces missing FVIII or FIX to prevent and control bleeds |
| Nonfactor therapy | Prevents bleeding without directly replacing the missing clotting factor |
| Bypassing agents | Control bleeds while bypassing the need for FVIII or FIX |
| Gene therapy | Helps the body produce healthy clotting factor |
| Supportive treatments | Help control specific types of bleeding |
Factor replacement therapy is the standard approach to treating hemophilia. However, some people on these medications — especially those with hemophilia A — eventually develop inhibitors, a type of neutralizing antibody against the clotting factor that can make the treatment less effective.
For such individuals, nonfactor therapies and bypassing agents are possible alternative treatment options. These medications help prevent and control bleeds in ways that don’t rely on the missing clotting factor.
Gene therapy is a newer, one-time treatment approach that provides the body with a working version of the gene that’s faulty in hemophilia, thereby restoring the production of the clotting factor. While this can provide long-term bleed prevention for some people, it is only available for certain adult patients.
How common is hemophilia?
Worldwide, it is estimated that around 850,000 people are living with some form of hemophilia. By hemophilia type, the disease is estimated to affect:
- hemophilia A: 17.1 per 100,000 males
- hemophilia B: 3.8 per 100,000 males
- hemophilia C: 1 in 100,000 people
Hemophilia prevalence may vary by geographical region, which can be related to genetic factors, as well as differences in healthcare systems, diagnostic tools, and reporting mechanisms. In the U.S., as many as 33,000 males are estimated to have hemophilia.
Acquired hemophilia is very rare, affecting an estimated 1.5 per every 1 million people each year. It mostly affects people older than 65.
Life expectancy
Historically, hemophilia was considered a fatal disease, and most people born with severe forms did not survive into adulthood. Modern treatments have dramatically changed this outlook. Now, people with hemophilia who are diagnosed and started on treatment at a young age have a life expectancy near what is seen in the general population.
For treated people with severe hemophilia A and B, life expectancy in developed countries is generally within 10 years of that seen in the general population. Life expectancy is typically normal for people with mild or moderate hemophilia, including hemophilia C. Still, a person’s prognosis can vary based on several factors, including disease type and severity, inhibitor development, lifestyle, access to treatment, and other health conditions.
There is no cure for hemophilia, and it requires lifelong care. With an appropriate treatment and monitoring plan, people with hemophilia can lead relatively normal lives.
Hemophilia News Today is strictly a news and information website about the disease. It does not provide medical advice, diagnosis, or treatment. This content is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website.



